A changed voice is not defined only by complete loss of speech. You will learn how to recognise the different patterns of voice change, when four weeks is too long to wait, which warning signs need faster assessment, and what an ENT evaluation can reveal.
Key takeaways
- Hoarseness lasting beyond two to four weeks needs medical assessment.
- Seek urgent care for breathing trouble, coughing blood, or difficulty swallowing.
- Do not assume reflux or infection is the cause without an examination.
- An ENT may recommend stroboscopy, imaging, biopsy, or voice therapy.
What Counts as Persistent Hoarseness?
A voice change counts as hoarseness when your usual sound becomes rough, raspy, breathy, strained, weak, or different in pitch. Hoarseness is a form of dysphonia, the clinical term for an abnormal voice, and does not require complete loss of voice.
Vocal fatigue also matters: your voice tires quickly, weakens during speaking, or requires unusual effort.
Arrange an adult ENT evaluation when the change lasts four weeks without clear improvement. Do not wait for loss of voice; persistent hoarseness needs assessment with laryngoscopy to examine the larynx. People who use their voice professionally should seek evaluation sooner because a small vocal-fold change can affect their work.
Arrange prompt assessment before four weeks if you smoke or have a history of heavy alcohol use. Seek urgent medical help for:
- Coughing blood, difficulty breathing, or noisy breathing
- Trouble swallowing or severe throat pain
- A neck lump
- Unexplained weight loss
- Ear pain when examination shows no ear problem
A stable or mild voice change is not proof that the cause is harmless, particularly for someone who smokes. Avoid waiting several months or treating the problem as routine reflux before the larynx has been examined.
Common Causes and Warning Signs That Change the Urgency
Acute laryngitis from a viral infection can leave the voice rough for days, while vocal overuse can inflame or injure the vocal folds. Persistent change also comes from reflux-related irritation, allergies, postnasal drainage, medication effects, or structural problems such as nodules, polyps, and cysts.
Listening cannot reveal whether the cause is inflammation, paralysis, neurologic disease, or a tumour.
| Cause | Clue | Usual urgency |
|---|---|---|
| Acute laryngitis | Sudden rough or weak voice with a cold | Review if it persists beyond four weeks |
| Vocal overuse | Voice worsens after prolonged speaking, singing, or shouting | Arrange assessment if rest does not restore it |
| Reflux-related irritation | Hoarseness with throat clearing or a lump sensation | Do not assume reflux without vocal-fold examination |
| Nodules, polyps, or cysts | Ongoing breathiness, strain, or pitch change | ENT assessment is needed |
| Vocal-fold paralysis | Breathy voice, weak cough, or choking on liquids | Prompt assessment |
| Smoking and hoarseness | Persistent change in a current or former smoker | Prompt ENT assessment; cancer must be excluded |
Seek prompt ENT assessment for coughing blood, difficulty breathing, noisy breathing or stridor, trouble swallowing, a neck lump, unexplained weight loss, severe throat pain, or ear pain without an ear finding. Heavy alcohol use or previous thyroid or neck surgery also lowers the threshold for referral.
Do not wait for complete voice loss: dysphonia lasting more than four weeks needs laryngoscopy, and breathing symptoms require urgent care.
Why Automatic Treatment Can Miss the Real Problem
Automatic treatment can miss the real problem because hoarseness describes a symptom, not its cause. A vocal nodule, polyp, cyst, vocal-fold paralysis, neurologic disorder, reflux-related irritation, medication effect, and laryngeal cancer do not share one treatment.
- Do not use antibiotics for hoarseness simply because the voice sounds rough. Most isolated dysphonia is not bacterial, so antibiotics add risks such as diarrhoea, allergic reactions, and antibiotic resistance without correcting a lesion or paralysis.
- Do not take steroids for dysphonia without an examination. Steroids can reduce swelling and create temporary improvement while a structural problem or cancer remains unrecognised; repeated courses also carry health risks.
- Do not start reflux medicine for every hoarse voice. Reflux treatment is not justified by isolated dysphonia alone, especially when the larynx has not been visualised and other causes remain possible.
- Do not treat voice rest as a complete solution. Voice rest can reduce strain, but it cannot remove a polyp, restore a paralysed fold, or diagnose inefficient voice production.
Arrange laryngoscopy when dysphonia lasts four weeks, or sooner for breathing difficulty, coughing blood, swallowing trouble, a neck lump, severe pain, or tobacco exposure. The examination identifies what treatment fits instead of allowing temporary symptom relief to delay necessary care.
What Happens During an ENT Voice Evaluation?
An ENT evaluation looks beyond how your voice sounds: it identifies what the vocal folds are doing. At four weeks of dysphonia, laryngoscopy is appropriate; earlier assessment matters if you smoke, use your voice professionally, or have concerning symptoms.
Your voice history covers onset, progression, intermittent versus constant symptoms, vocal demands, recent infection, smoking and alcohol exposure, reflux symptoms, allergies, medications, and previous intubation or neck surgery. Tell the clinician about pain, swallowing or breathing changes, coughing blood, and a neck lump.
Listening to speech helps characterize breathiness, strain, pitch change, fatigue, or loss of voice, but it cannot reveal the cause by itself.
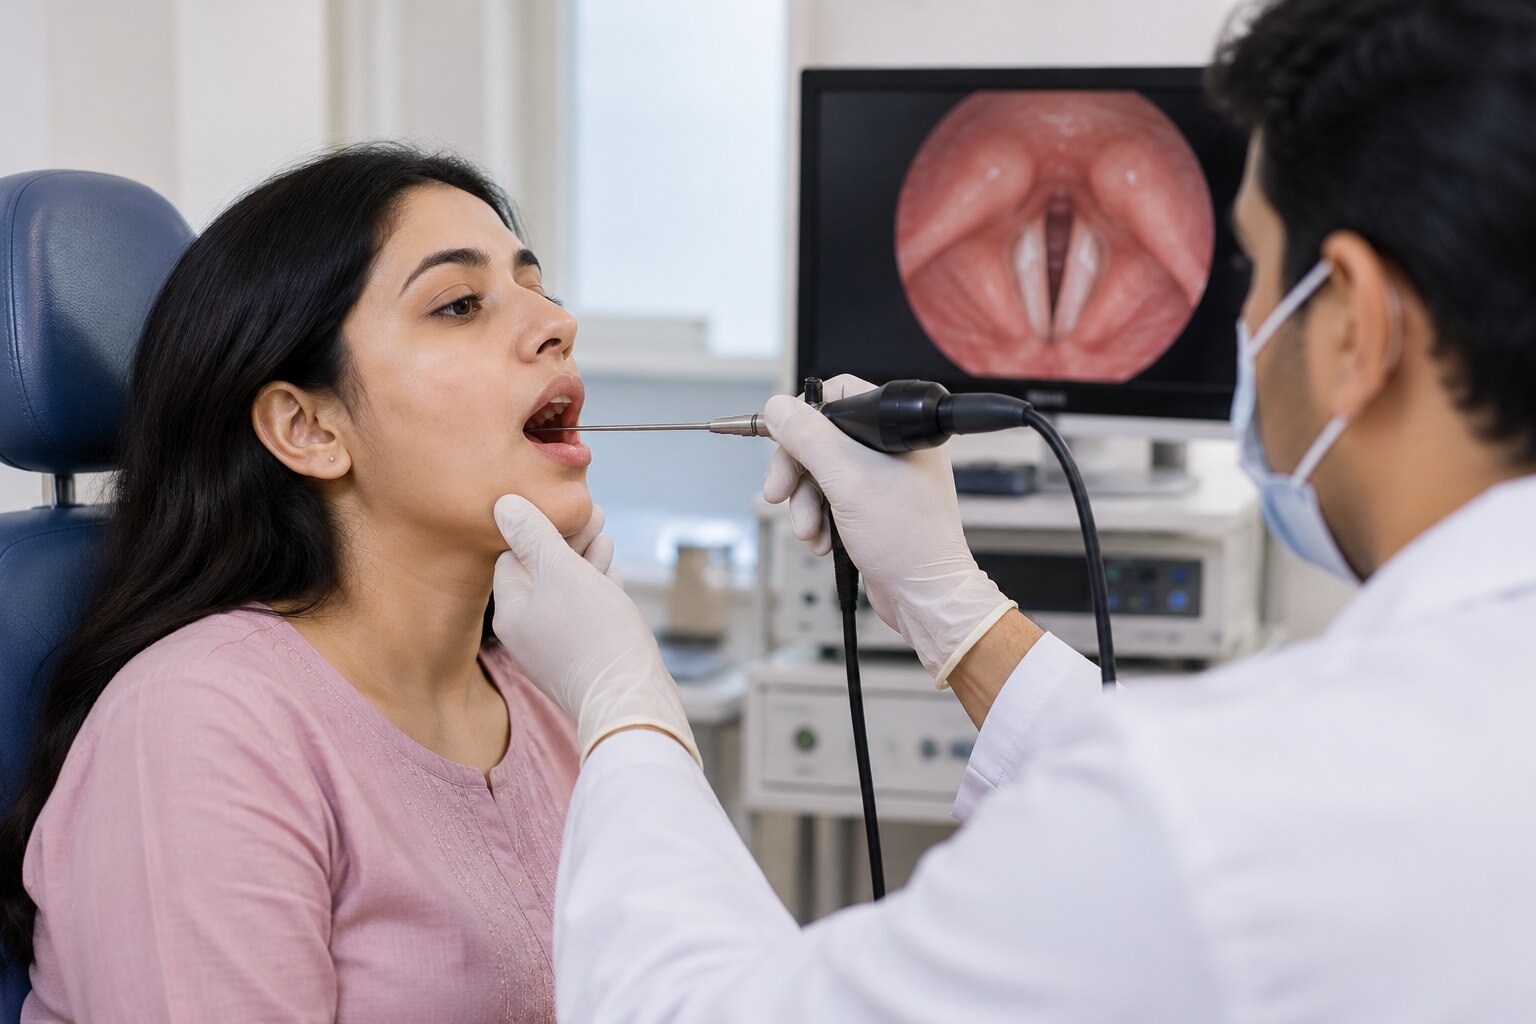
The clinician examines your mouth, throat, and neck, then performs flexible transnasal laryngoscopy in the office in many cases. During this flexible laryngoscopy, a narrow camera passes through one nostril to view the larynx while you breathe, speak, and sometimes change pitch. It shows vocal-fold movement, closure, surface changes, swelling, and anything needing closer assessment.
The scope also helps identify weakness or paralysis that listening alone would miss. CT or MRI is not usually the starting point for an isolated voice complaint; the laryngeal findings determine whether imaging is needed and which area to scan.
When You Need Stroboscopy, Imaging, Biopsy, or Voice Therapy
A normal-looking static examination does not end the investigation if your voice remains unexplained. The ENT clinician matches the next step to what was seen, how long symptoms have lasted, and whether you are a professional voice user whose work depends on subtle vocal changes.
| Option | What it adds | When it applies |
|---|---|---|
| Videostroboscopy | Shows vocal-fold vibration and the mucosal wave in slow motion | When ordinary laryngoscopy misses a subtle lesion or does not explain the symptom |
| CT or MRI for hoarseness | Maps deeper structures, nerves, the neck, or a mass | After laryngoscopy identifies a reason and the region requiring imaging |
| Vocal-fold biopsy | Identifies abnormal tissue under laboratory examination | When a lesion looks suspicious, persists, enlarges, or requires tissue diagnosis |
| Speech-language pathology | Uses targeted techniques to reduce inefficient or traumatic voice production | When the folds are suitable for behavioral treatment after examination |
Do not treat voice therapy as simple voice rest. A speech-language pathologist may address breath support, muscle tension, vocal habits, and load; therapy is unsafe as a substitute for examining the folds first.
CT or MRI for hoarseness is not usually the first test for an isolated complaint. Imaging before laryngoscopy can miss the actual surface problem and answer the wrong anatomical question.
Dr.Phadke’s ENT & Rhinoplasty Clinic-08048038595 can be considered when an ENT evaluation identifies a lesion requiring discussion of microsurgical treatment; that decision should follow the examination, not the sound of the voice alone.
Related service
Best Micro Laryngeal Surgery Specialist in Bavdhan,Pune & PCMC If you are searching for the best Micro Laryngeal Surgery specialist in Pune and PCMC, Dr Aniruddha Phadke at Dr Phadke’s ENT Clinic is a trusted... View service → |
Frequently asked questions
What counts as persistent hoarseness?
Hoarseness is a rough, raspy, breathy, strained, weak, or pitch-changed voice. It becomes persistent when the change does not resolve within the expected time for a short-lived illness, especially when it lasts two to four weeks.
Which warning signs make hoarseness more urgent?
Breathing difficulty, coughing blood, trouble swallowing, a neck lump, unexplained weight loss, severe pain, or a history of tobacco use requires prompt ENT evaluation.
Why can automatic treatment miss the real cause of hoarseness?
Reflux medicine, antibiotics, or voice rest cannot treat every cause. Hoarseness can result from vocal-fold lesions, nerve problems, muscle tension, irritation, or other conditions that require direct examination.
What happens during an ENT voice evaluation?
The ENT reviews your voice history, symptoms, medications, tobacco exposure, and voice use, then examines your throat and vocal folds. The clinician may recommend a flexible laryngoscopy or another test.
When are stroboscopy, imaging, biopsy, or voice therapy needed?
Stroboscopy assesses vocal-fold vibration when a routine examination does not explain the voice change. Imaging evaluates selected structural or nerve-related concerns, biopsy examines suspicious tissue, and voice therapy helps treat appropriate functional or vocal-fold problems.